Diabetic Foot Warning Signs: When to Go to Hospital Today
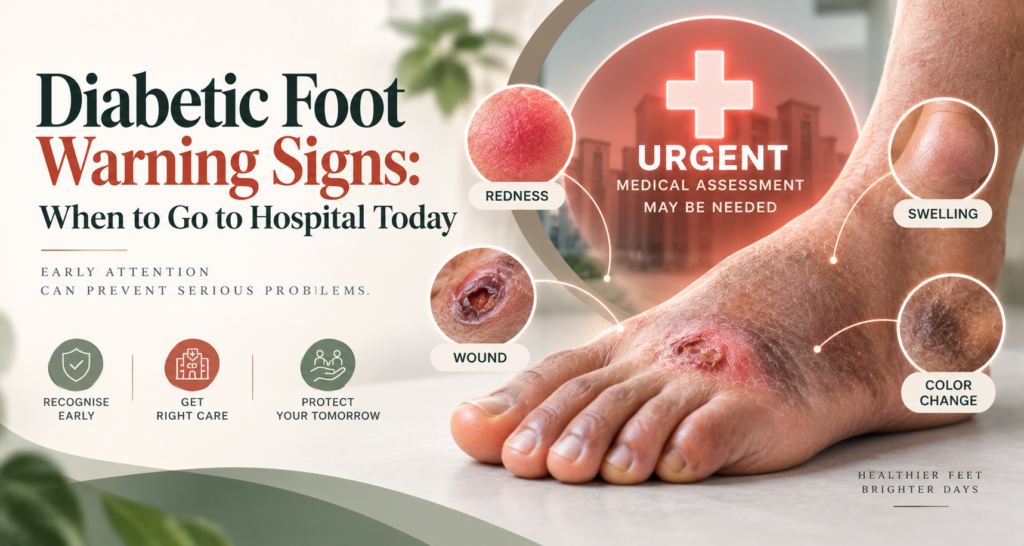
Some diabetic foot warning signs need same-day medical attention, especially rapidly spreading redness or swelling, black or dead-looking tissue, pus with worsening infection, fever or chills, a deep wound, or a sudden cold or discoloured foot. A diabetic foot problem can also be serious without pain because nerve damage may reduce sensation.
For someone with diabetes, a blister, crack, shoe bite or small wound should not automatically be treated like an ordinary foot injury.
Diabetes can affect sensation and blood circulation. This means a patient may not notice an injury early, and an open wound can become more difficult to heal or become infected.
The American Diabetes Association recommends urgent referral for people with diabetes who have any open ulceration or unexplained swelling, redness or increased skin temperature in the foot.
Knowing when to seek help is therefore an important part of diabetic foot care.
Which Diabetic Foot Warning Signs Mean You Should Go to Hospital Today?
Some symptoms should not wait for a routine appointment.
The following table gives patients and families a practical way to think about urgency.
Diabetic Foot Warning Signs: Three-Tier Triage
| Go Today / Same-Day Medical Assessment | Be Seen Within 48 Hours | Book a Routine Appointment |
|---|---|---|
| Rapidly spreading redness, warmth or swelling | A new small open wound or ulcer without rapidly worsening signs | Thick callus without bleeding or an open wound |
| Black, grey, blue or dead-looking tissue | A new blister, skin crack or shoe injury | Dry skin without a wound |
| Pus or increasing discharge with redness or swelling | Blood or dark staining beneath a callus | Thick nails needing professional diabetic foot care |
| Fever, chills or feeling unwell with a foot wound | Localised redness or warmth that is not progressing rapidly | Stable nail or fungal changes without an ulcer |
| A deep wound or visible deeper tissue | A wound that is not improving as expected | Routine footwear or pressure assessment |
| Suspected deep abscess or rapidly deteriorating wound | Recurrent blistering or pressure marks | Routine diabetic foot screening |
| Sudden cold, pale, blue or significantly discoloured foot | A minor wound in someone with previous ulcers, neuropathy or poor circulation | Stable foot deformity without skin breakdown |
| Gangrene or severe tissue damage | Any new wound whose severity is difficult to judge because the foot is numb | Preventive review in a high-risk diabetic foot |
This table is a guide, not a diagnosis. If a foot is deteriorating quickly, the person is becoming unwell, or there is uncertainty about the severity, medical assessment should not be delayed.
IWGDF guidance recommends urgent surgical consultation for severe diabetic foot infection and for moderate infection complicated by extensive gangrene, necrotising infection, signs of a deep abscess, compartment syndrome or severe lower-limb ischaemia.
Dr. Shah should review and approve the exact placement of symptoms in these three tiers.
What Does a Spreading Diabetic Foot Infection Look Like?
A diabetic foot infection can begin around an ulcer, cut, blister or other break in the skin.
Possible diabetic foot infection signs include:
- Redness around the wound
- Increasing warmth
- Swelling
- Pus or discharge
- Worsening wound appearance
- Increasing tissue damage
- Unpleasant or foul-smelling discharge
- Redness spreading beyond the original wound
- Fever, chills or feeling generally unwell
An infection may start in the skin and soft tissues. In more serious cases, it can extend into deeper tissues or bone.
Current IWGDF guidance treats severe infections and moderate infections with gangrene, deep abscess or severe ischaemia as situations requiring urgent specialist involvement. For selected moderate or severe infections, early surgery within 24 to 48 hours may be considered to remove infected and necrotic tissue.
What Does Poor Circulation in a Diabetic Foot Look Like?
Poor blood circulation can make a diabetic foot wound more serious because damaged tissues need adequate blood flow for healing.
Changes that should raise concern include:
- A foot becoming unusually cold
- New pale or blue colour
- Dark or black tissue
- A wound that continues to deteriorate
- Tissue loss
- A wound that is failing to heal
- Rest pain in some patients
A person should not try to diagnose circulation simply by looking at the foot.
A suddenly cold, pale, blue or markedly discoloured foot needs urgent medical assessment.
The urgency becomes even greater when poor circulation and infection occur together. IWGDF guidance recommends urgent surgical and vascular consultation when a person with diabetes has peripheral artery disease together with a foot ulcer or gangrene and infection.
Why Can a Painless Diabetic Foot Wound Still Need Urgent Care?
A common and dangerous assumption is:
“There is no pain, so the wound cannot be serious.”
Diabetic peripheral neuropathy can reduce protective sensation.
The patient may not properly feel:
- A shoe bite
- A blister
- Excessive pressure
- A cut
- Heat
- An open wound
This means damage can continue while a person keeps walking normally on the affected foot.
The ADA identifies loss of protective sensation as an important diabetic foot risk factor and recommends urgent specialist referral when an open ulcer, unexplained swelling, redness or increased skin temperature develops.
So when deciding when to see a doctor for a foot ulcer, pain should never be the only deciding factor.
A painless wound still deserves appropriate assessment.
Which Diabetic Foot Changes Should Be Seen Within 48 Hours?
Some changes may not have the severe warning signs described above but still should not be ignored for several days.
These can include:
- A new small ulcer
- A new blister
- A crack that has broken the skin
- A shoe bite
- Blood appearing under a callus
- New localised redness
- Repeated pressure damage
- A wound that is not progressing normally
Prompt review is particularly important for someone who already has:
- Diabetic neuropathy
- Poor circulation
- A previous foot ulcer
- A previous toe or foot amputation
- Significant foot deformity
- Recurrent foot wounds
The ADA states that people with moderate to high foot risk should receive specialist evaluation and ongoing surveillance, while an open ulcer or unexplained redness, swelling or increased temperature requires urgent referral.
This is why a new wound should not be watched indefinitely simply because it is small.
Which Foot Changes Can Usually Wait for a Routine Appointment?
Routine diabetic foot care is important because many problems are safer to address before the skin breaks down.
Examples can include:
- Thick callus without an open wound
- Dry or cracked skin without bleeding
- Thickened toenails
- Stable fungal nail problems
- Foot deformity without skin breakdown
- Routine footwear assessment
- Preventive diabetic foot screening
These changes are not necessarily emergencies, but they should not be ignored.
Patients with diabetes should avoid cutting calluses or treating risky foot problems themselves. Preventive care, appropriate footwear and regular foot examination can help identify areas at risk before an ulcer develops. The ADA advises daily inspection and avoiding self-care of ingrown nails and calluses in at-risk patients.
If a routine problem develops bleeding, redness, swelling, discharge or an open wound, its urgency changes.
Can I Wait Until Monday With a Diabetic Foot Ulcer?
Not always.
If you notice a diabetic foot problem on a weekend, do not decide to wait until Monday simply because your usual clinic is closed.
Seek same-day medical attention if there is:
- Rapidly spreading redness
- Significant or rapidly increasing swelling
- Black or dead tissue
- Gangrene
- Severe discharge with worsening inflammation
- Fever or chills
- A deep wound
- Suspected abscess
- Sudden colour or temperature change
- Rapid deterioration
IWGDF guidance specifically recommends urgent specialist consultation for severe infection and certain complicated moderate infections.
A stable new wound without these severe features still deserves prompt professional assessment rather than prolonged observation at home.
What If There Is a Smell From the Diabetic Foot Wound?
A foul smell from a diabetic foot wound should not be ignored, particularly when it appears together with:
- Pus or discharge
- Increasing redness
- Swelling
- Warmth
- Black or unhealthy tissue
- Increasing wound depth
- Fever or illness
Smell alone cannot tell you exactly how deep or severe an infection is.
A clinician needs to examine the wound and decide whether there is infection, dead tissue, poor circulation or another cause.
If the smell is new or the wound is worsening, arrange medical assessment rather than trying to hide the smell with powders, creams or home remedies.
What Should You Do While Arranging to Be Seen?
The purpose of first steps is to protect the foot until appropriate medical care is available, not to replace medical assessment.
While arranging care:
- Reduce pressure on the affected foot. Avoid unnecessary walking on the wound.
- Protect an open wound with a clean dressing if one is available.
- Do not walk barefoot.
- Do not cut the wound, callus or dead-looking tissue yourself.
- Do not puncture or squeeze swollen areas.
- Do not apply toothpaste, turmeric, oils, herbal pastes or other home remedies instead of seeking care.
- Do not use leftover antibiotics without medical advice.
- Watch for rapid changes while arranging assessment.
- If the foot worsens or the person becomes unwell, seek more urgent medical help.
Antibiotics are not automatically needed for every diabetic foot ulcer. IWGDF guidance recommends diagnosing diabetic foot infection clinically and specifically advises against treating a clinically uninfected ulcer with antibiotics simply to promote healing or prevent infection.
For detailed international guidance, see the official IWGDF Guidelines on the Prevention and Management of Diabetes-Related Foot Disease.
Why Does Early Diabetic Foot Assessment Matter?
A diabetic foot specialist does more than look at the surface of the wound.
Assessment may involve checking:
- Wound depth
- Infection
- Blood circulation
- Protective sensation
- Pressure on the ulcer
- Foot deformity
- Dead or unhealthy tissue
- Possible bone involvement
- Need for pressure relief
- Need for vascular or surgical treatment
This matters because two wounds that look similar from the outside can have very different problems underneath.
The site’s main diabetic foot ulcer page explains these causes, assessment methods and treatment options in more detail.
Diabetic Foot Ulcer: Causes, Stages and Treatment in India
Get a Diabetic Foot Wound Checked in Surat
A diabetic foot wound should not be judged only by how painful it is or how small it looks.
New wounds, spreading infection, swelling, colour changes and possible poor circulation deserve timely assessment. Reduced sensation may hide the seriousness of a problem.
At Elegance Diabetic Foot And Ulcers Clinic, Surat, diabetic foot care includes wound assessment, infection management, pressure reduction, circulation assessment and surgical or reconstructive treatment when clinically required. The clinic’s published contact number is +91 88490 66499.
If you have an open diabetic foot wound or are unsure whether a change is urgent, arrange an assessment rather than waiting for the problem to become painful.
Book an appointment: /form
Call: +91 88490 66499
Frequently Asked Questions
Not every diabetic foot ulcer requires emergency hospital treatment, but every new ulcer deserves timely assessment. Spreading infection, gangrene, severe tissue damage, deep abscess, severe poor circulation or systemic illness can require same-day specialist care.
An infected ulcer may have increasing redness, warmth, swelling, pus or other discharge. The wound may worsen or redness may begin spreading. More serious infection can involve deep tissue, gangrene, fever, chills or general illness.
Diabetic neuropathy can reduce protective sensation. A patient may therefore have a significant blister, ulcer or other injury with surprisingly little pain. Lack of pain should not be taken as proof that the wound is minor.
Do not automatically wait if the foot is rapidly worsening. Spreading redness, major swelling, gangrene, black tissue, fever, deep infection or sudden changes in colour or circulation need more urgent assessment.
A new foul smell, particularly with discharge, redness, swelling or unhealthy-looking tissue, should be medically assessed. Smell alone cannot determine the severity of an infection.
Protect the wound with a clean dressing if available and reduce pressure on it while arranging medical assessment. Avoid unprescribed remedies, cutting tissue yourself or delaying care to try a home treatment.